
Feature | Getting to Goals: Applying the 2026 Dyslipidemia Guideline in High-Risk Patients
New evidence-based risk assessment and treatment algorithms were introduced in the 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/ AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia.1 Some of the biggest changes impact primary prevention, including 1) the addition of chronic kidney disease (CKD) and HIV as groups with statin indications without the need for further risk assessment (joining those with diabetes or LDL-C ≥190 mg/dL); 2) risk assessment for all others without ASCVD based on PREVENT algorithms starting a decade earlier at age 30; 3) new cut-offs for low-, borderline-, intermediate and high-risk primary prevention; 4) additional personal risk factors that justify consideration of statin initiation in borderline and intermediate risk groups; and 5) recommendations for expanded coronary artery calcium (CAC) testing and universal Lp(a) screening.
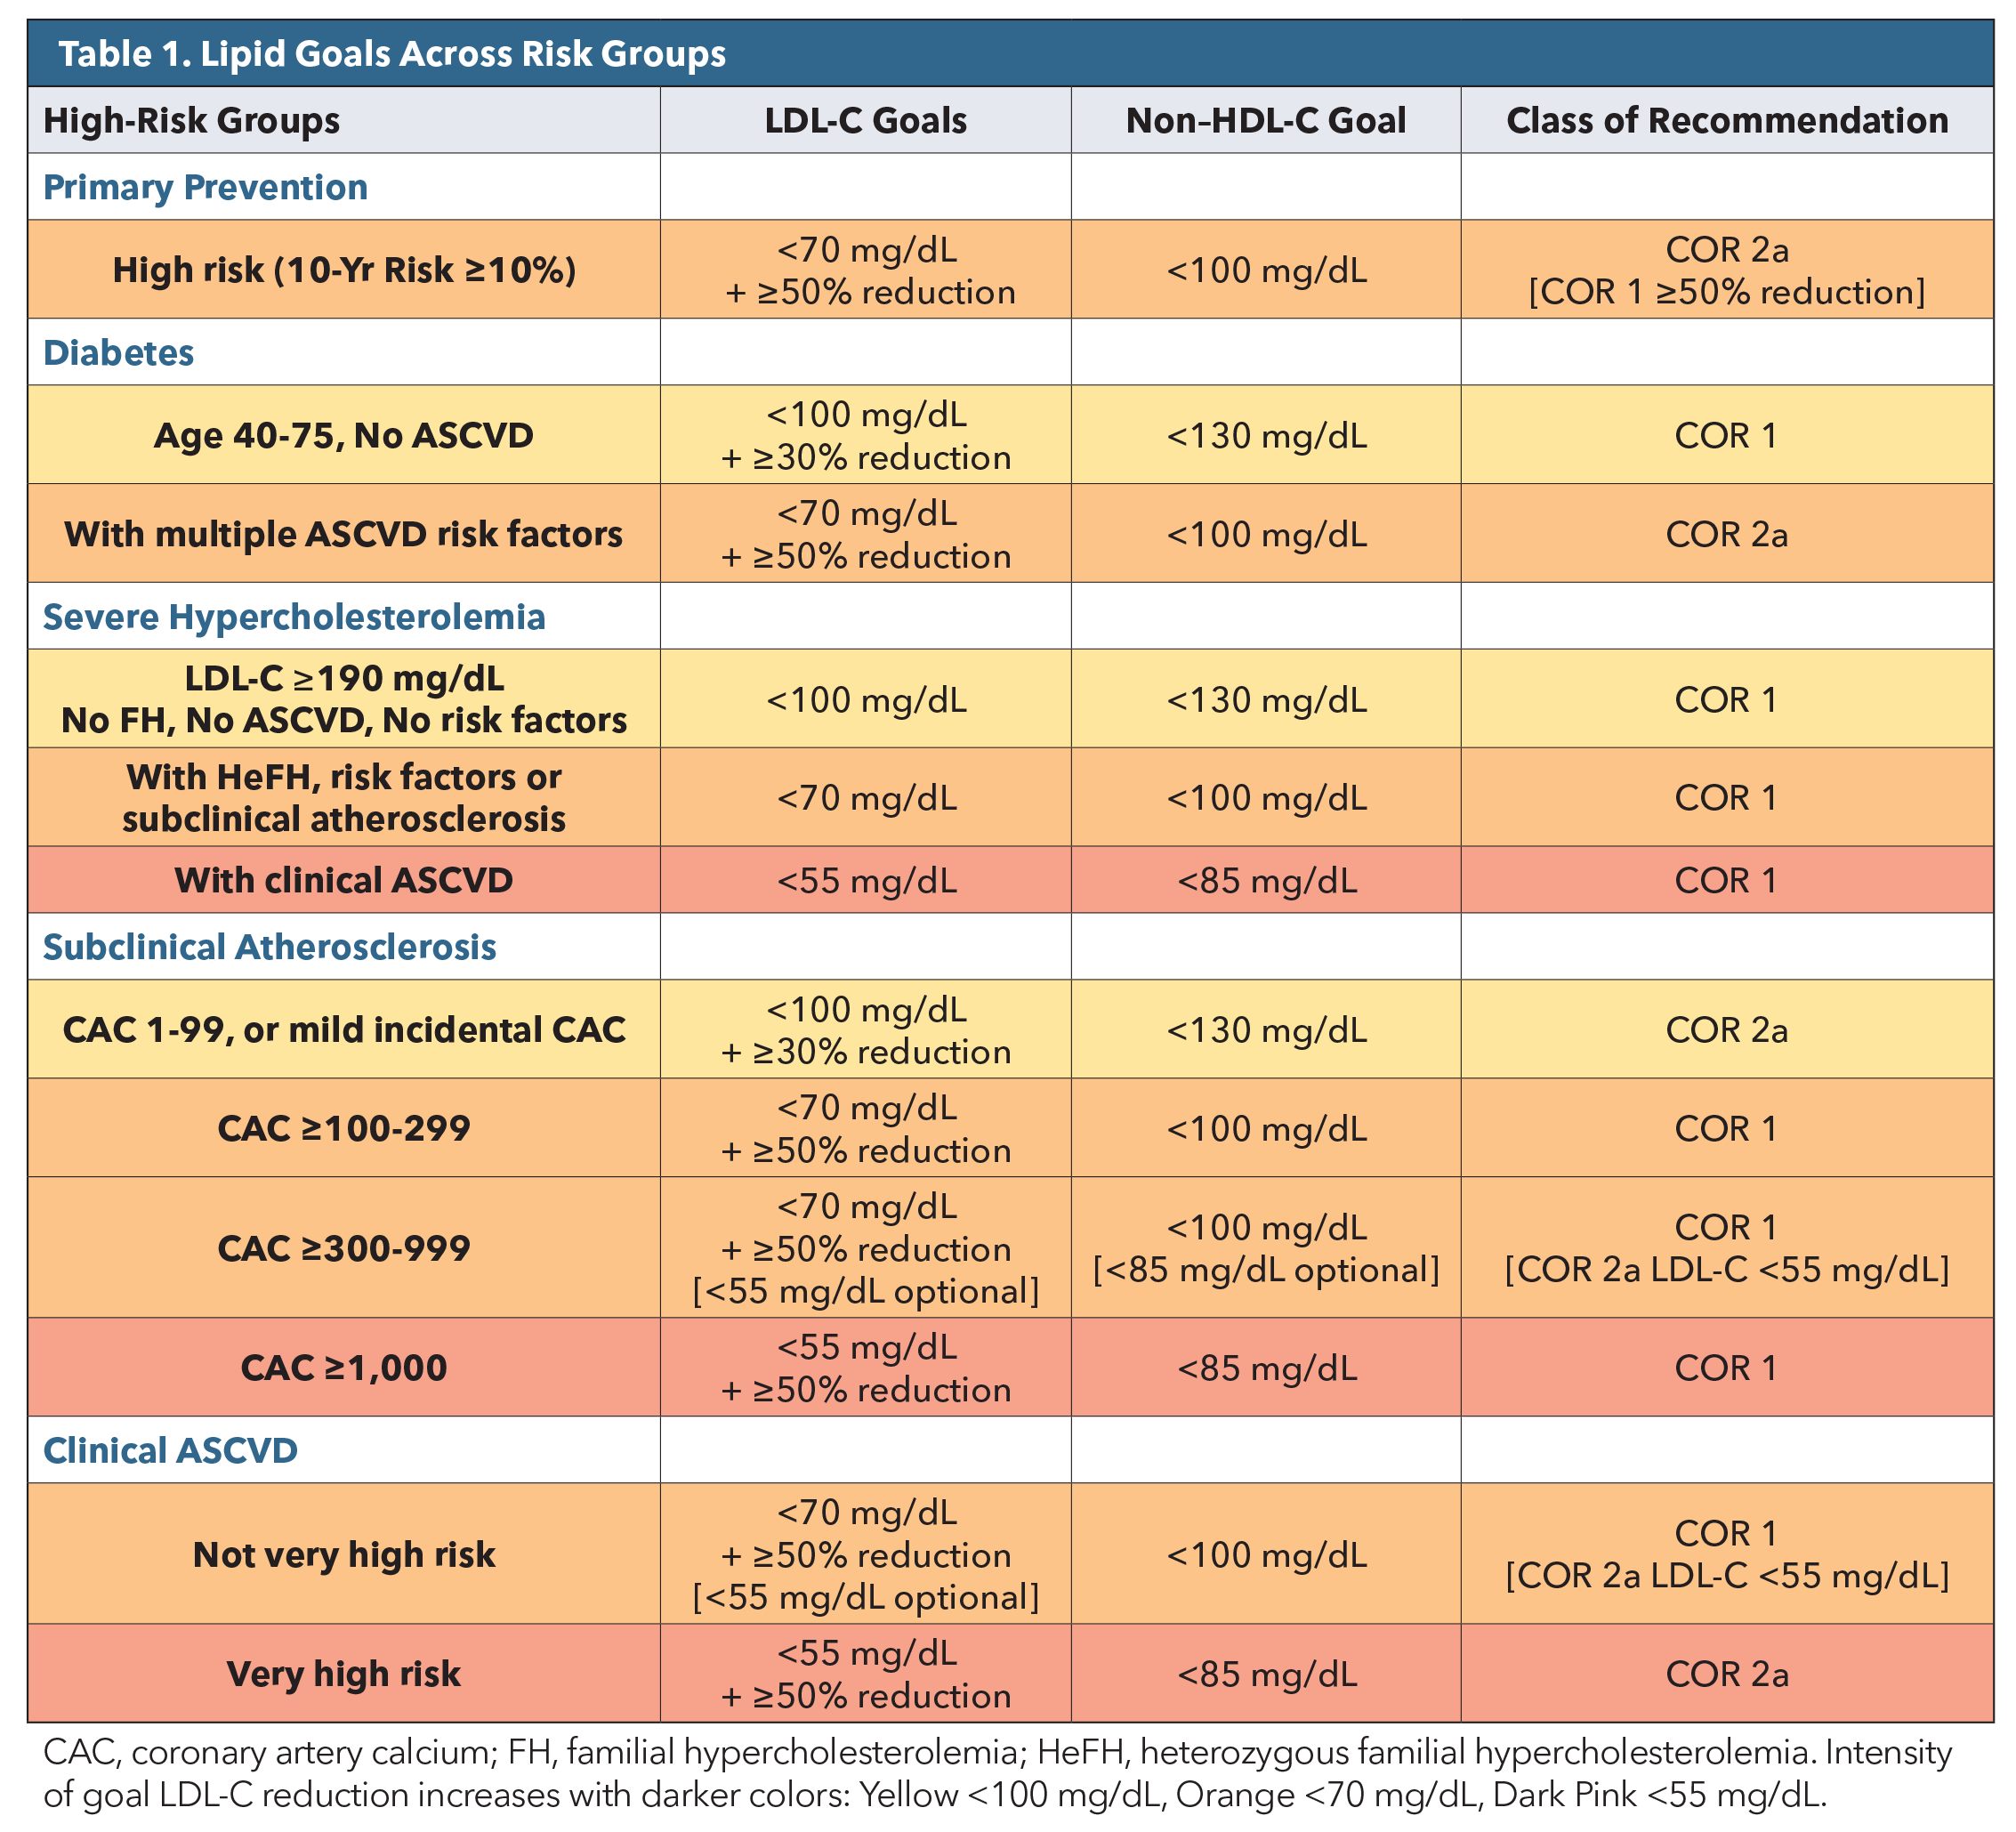
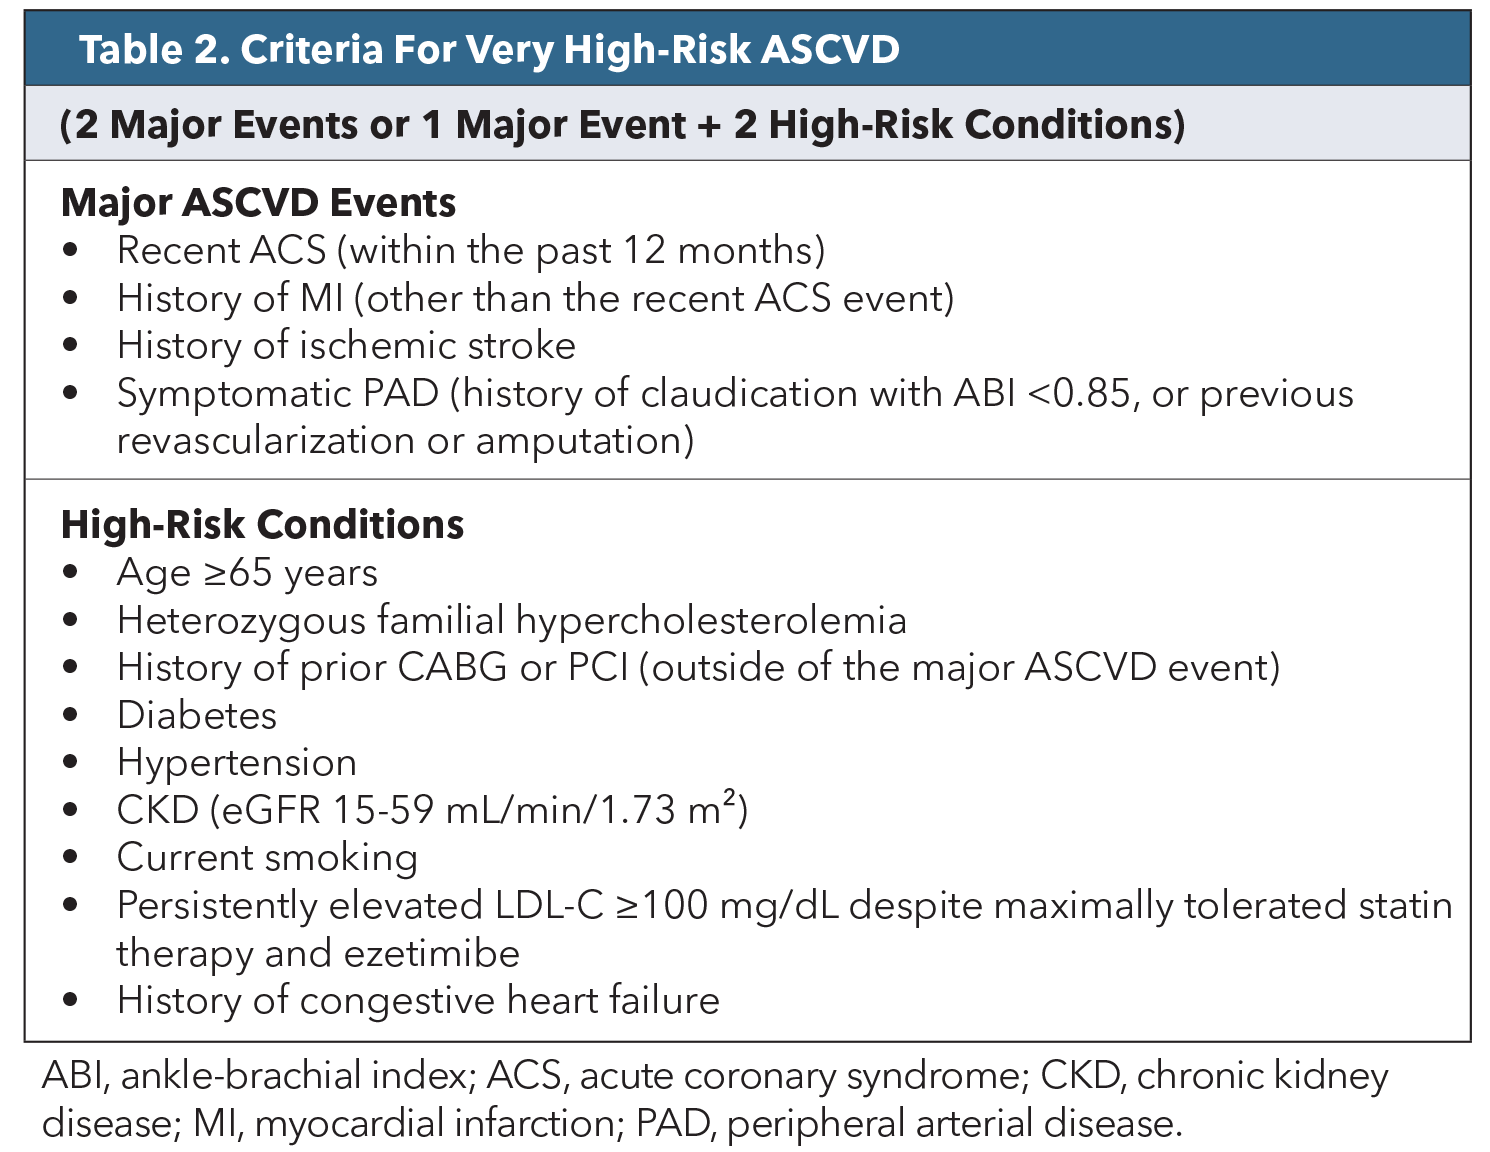
Other guideline changes, however, will have larger impacts in secondary prevention. This includes the reestablishment of absolute goals for LDL-C <70 mg/dL and non–HDL-C <100 mg/dL in all with subclinical or clinical ASCVD, and a more ambitious LDL-C goal of <55 mg/dL and non–HDL-C goal of <85 mg/dL in 'very high-risk ASCVD.' In addition, there is 1) a reemphasis on achieving at least a 50% percent reduction in LDL-C in most high-risk groups; 2) an optional Apo-B goal in conditions associated with increased remnant lipoproteins; 3) new medication and lifestyle recommendations for residual hypertriglyceridemia; and 4) a greater emphasis on nonstatin add-on therapies for lipid goal attainment, especially in the high risk.
The return to absolute lipid goals (de-emphasized after the 2013 guideline) is a welcome reset in those with ASCVD. Recent U.S. claims and registry data show that large proportions with established ASCVD continue to remain above previously recommended LDL-C goals even after myocardial infarction (MI),2-4 a gap linked to higher event rates and health costs. Although a complex interplay of clinician, patient, health system and policy/regulatory barriers drives 'therapeutic inertia' in lipid management,5,6 many scalable solutions now exist for overcoming these.
Overcoming Clinician Barriers to Lipid Goal Attainment
Gaps in clinician knowledge and training, coupled with time constraints and uncertainty about treatment benefits vs. risks have been linked to therapeutic inertia and slow lipid guideline adoption.5 Lack of lipid testing by clinicians also has been identified in large numbers of patients not achieving LDL-C goals, while the converse, checking and providing follow up lipid levels, has been found to improve lipid goal attainment.6
Clinicians can overcome this barrier by knowing the new guideline's nuanced lipid goals especially across high-risk categories (Table 1), disseminating them to colleagues, referring providers and patients, and ordering lipid testing and follow-up. Clinicians should also know new criteria for 'very high-risk ASCVD' (Table 2) and document the need for lowering LDL-C to <55 mg/dL and non–HDL-C to <85 mg/dL in this broad patient group.
Patients who question whether low LDL-C poses health risks will benefit from a discussion of the science that supports the 'lower is better' strategy. Institutional laboratories that still flag LDL-C under 70 mg/dL as 'low' can usually be engaged to remove the alert.
Additionally, clinicians should know the criteria for Apo-B testing after LDL-C is at goal, which includes residual hypertriglyceridemia and/or diabetes. They should also test for and document elevated Lp(a) levels, and if present recommend family screening and, if ≥125 nmol/L or ≥50 mg/dL, recommend early control of all risk factors including LDL-C to <70 mg/dL. Note, if ASCVD is also present and LDL-C and non–HDL-C are above goals on maximally tolerated statin therapy, a Class I recommendation now exists to add a PCSK9 monoclonal antibody,1 which also lowers Lp(a) modestly.
Finally, clinicians should know add-on lipid therapies and sequencing strategies (Box Below). Note that patients with suboptimal diets and LDL-C and non–HDL-C levels only slightly above goals are likely to achieve them by dietary measures (reducing saturated fat and increasing fiber-rich plant-foods), with referral to a dietitian if needed also a recommendation of the new guideline. In contrast, those practicing healthy diets with high baseline LDL-C and/or very large gaps in goal attainment will need combination therapy.
Roger S. Blumenthal, MD, FACC, preventive cardiologist, director of the Johns Hopkins Ciccarone Center for the Prevention of Cardiovascular Disease and lead guideline author notes, "We now have lots of tools in the toolbox for achieving target LDL-C levels compared to a decade ago. We have multiple treatment classes to choose from, just like we do for managing blood pressure."

Overcoming Patient Barriers to Lipid Goal Attainment
Patient barriers to lipid goal achievement are significant and include perceived or real 'statin attributed muscle symptoms' (SAMS); lack of understanding of the treatment rationale; interacting medications or comorbidities that limit the use of high intensity statins; severe hypercholesterolemia at baseline; lifestyle factors that worsen hyperlipidemias; and socioeconomic factors and cost barriers.
SAMS are pervasive in the real world. In the 2012 USAGE study of >10,000 statin users,12% had stopped statins and 62% reported SAMS or other side effects as the principal reason.7 However, the prevalence of true SAMs is now estimated to be lower, at around 5%, after the 2021 SAMSON and STATINWISE trials showed no significant differences in myalgia during placebo- vs. statin-treatment.8,9
Clinicians can address SAMS by 1) knowing the factors that predict true SAMS;10 2) reassuring patients that the likelihood is low that symptoms are truly statin-related; 3) offering to tailor therapy and check muscle enzymes with each lipid test; and 4) using low, nondaily doses of the two statins with the longest half-lives (rosuvastatin and atorvastatin) taken with better hydration. Note that some patients will need to fully trust a clinician before agreeing to be rechallenged.

Low patient understanding of the rationale for statin treatment is also common. In the USAGE study, two of three patients who stopped statins reported being unaware that treatment reduces the risk of MI, and a large proportion had read online stories about statins before stopping them.7 These data underscore the importance of patient education when prescribing statins. "Conveying that statins can help 'keep arteries open' and 'prevent heart attacks' may resonate more than just saying they lower cholesterol," notes Karen Aspry, MD, MS, FACC, a lipid specialist, cardiologist, and director of the Lipid and Prevention Program at Brown University Health Cardiovascular Institute. Evidence exists that coronary calcifications and carotid plaque on imaging can improve lipid medication usage.11,12
Medication interactions and comorbidities also play roles in statin discontinuation. In the USAGE study, large proportions who discontinued statins had been on medications that had potential statin interactions.7 However, this risk can be mitigated. "Rosuvastatin, pravastatin, pitavastatin and fluvastatin tend to be better tolerated than others due to their mechanisms of metabolism," notes Blumenthal.
Low BMIs, CKD, hepatic dysfunction, increased age and being a genetically 'slow metabolizer' can also lead to statin intolerance and discontinuation but can be mitigated by reduced and/or nondaily dosing. These and other solutions can be found in the 2022 NLA Scientific Statement on statin intolerance.10
Overcoming Health System and Policy Barriers to Lipid Goal Attainment
Traditional care models that lack infrastructures for disease management and population health management are poorly equipped to improve lipid goal attainment in large panels of patients. However, integrated health systems (i.e., Kaiser, Geisinger and the Veteran Affairs health systems) and academic institutions transitioning to accountable care organizations have successfully utilized clinical information systems and collaborative care (by pharmacists, nurse specialists and nonlicensed trained health personnel) to achieve and maintain improved lipid outcomes.13-15

Many others have instituted pharmacist support to improve medication access to the growing number of advanced lipid therapies. Maintaining patients on these medications should get easier for all health systems. "The growing availability of programmable EHR's that can detect high-risk patients not at goals, and of collaborative care for closing these gaps, should improve lipid goal attainment for all," notes Aspry. "However, policy support will still be needed. Now that we have an LDL-C goal again in those with ASCVD, we must work towards restoring a national outcomes measure for LDL quality."16
Add-On Lipid Treatments and Sequencing Strategies
Statins are first line agents for lipid lowering, except when triglycerides (TGs) are ≥ 1,000 mg/dL. Treatment intensification with the LDL-C lowering agents below is indicated when LDL-C or non-HDL-C are not at goals on maximally tolerated statin therapy and a healthy diet. Treatment with the TG- lowering agents below is indicated first whenever TGs are ≥ 1,000 mg/dL, or as add-on agents for residual TG elevation after a maximally-tolerated high intensity statin and diet intervention, with the caveats below.
Cholesterol Absorption Inhibitor Ezetimibe
Lowers LDL-C by a median of 18% when used as monotherapy and by 25% when combined with a statin. Remains the first add-on agent due to its low cost. "Even when a high intensity statin is taken only 2-3 times per week, adding ezetimibe can reduce LDL-C by 40-50% from baseline," comments Blumenthal. "The recent EZ-PAVE trial adds to existing evidence that adding ezetimibe to a statin reduces LDL-C and ASCVD events," notes Aspry.
ATP-Citrate Lyase Inhibitor Bempedoic Acid
Lowers LDL-C by a median of 40% when combined with ezetimibe, 21-24% as monotherapy, and 17-18% when added to a statin. Aso reduces hsCRP. Reductions in MACE were demonstrated in the CLEAR OUTCOMES trial.
PCSK9 Inhibitor Monoclonal Antibodies Alirocumab and Evolocumab
Lowers LDL-C by a median of 45- 64%. Self-dosed subcutaneously twice monthly. Reduces MACE as monotherapy or when added to a statin. For those with severe hypercholesterolemia or ASCVD with elevated Lp(a), adding a PCSK9 inhibitor to statin therapy as the first step in treatment escalation is reasonable, but drug plans may require addition of ezetimibe first. Oral PCSK9 inhibitor enlicitide could broaden use.
PCSK9 Inhibitor Small-Interfering mRNA Inclisiran
Lowers LDL-C by a median of 48-52%. Dosed subcutaneously in a health center twice yearly after year one. Outcomes data are pending. "May be a reasonable option for patients with Medicare, as coverage is quite good," notes Blumenthal.
Angiopoietin-like protein 3 Monoclonal Antibody Inhibitor Evinacumab
Lowers LDL-C by a median of 49%. Infused once monthly. Approved for patients with homozygous FH.
Bile Acid Sequestrants Colesevelam and Others
Lower LDL-C 10-27%. Safe in pregnancy. One pre-statin outcomes trial in men demonstrated reduced MACE.
Fibrates Fenofibrate and Gemfibrozil
Lower TGs 30-50%. First line option when TG is ≥ 1,000 mg/dL to reduce pancreatitis risk. MACE reduction data for fenofibrate is limited. Avoid gemfibrozil with statins. Avoid both fibrates in CKD.
Omega-3-Fatty Acids Icosapent Ethyl (EPA only) and Omega-3-Acid Ethyl Esters (EPA and DHA)
Lowers TGs 15-61%. Consider for residual TG elevation after statin and diet. EPA-only formulation approved to reduce MACE in ASCVD or DM2 with TG 150-499 mg/dL.
Apo-CIII Antisense Oligonucleotide Olezarsen
Lowers TGs by a median of 42.5 % vs. placebo. Self-administered once monthly subcutaneously. Approved for patients meeting clinical or genetic criteria for familial chylomicronemia syndrome. Reduces risk of pancreatitis.
The editors-in-chief thank Karen Aspry, MD, MS, FACC, and Roger S. Blumenthal, MD, FACC, for their substantial contributions to this article.
References
- Blumenthal RS, Morris PB, Gaudino M, et al. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS /APhA/ASPC/NLA/PCNA guideline on the management of dyslipidemia: A report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. JACC. 2026;S0735-1097(25)10254-4. doi: 10.1016/j.jacc.2025.11.016.
- Navar AM, Kolkailah AA, Gupta A, et al. Gaps in guideline-based lipid-lowering therapy for secondary prevention in the United States: A retrospective cohort study of 322 153 patients. Circ Cardiovasc Qual Outcomes. 2023;16(8):533-543.
- Navar AM, Electricwala B, Multani JK, et al. Lipid management in United States commercial and Medicare enrollees with atherosclerotic cardiovascular disease: Treatment patterns and low-density lipoprotein cholesterol control. Am J Cardiol. 2025;242:1-9.
- Arnold SV, de Lemos JA, Liu Y, et al. Adherence to guideline medication recommendations to prevent ASCVD progression among adults with prior myocardial infarction. JAMA Network Open. 2020;3(4):e203032.
- Vatri M, Faggiano A, Angelino E, et al. Therapeutic inertia in lipid lowering treatment: A narrative review. J Clin Med. 2026;15(3):1075.
- Rana JS, Virani SS, Moffet HH, et al. Association of low-density lipoprotein testing after an atherosclerotic cardiovascular event with subsequent statin adherence and intensification. Am J Med. 2022;135(5):603-606.
- Cohen JD, Brinton EA, Ito MK, Jacobsen TA. Understanding Statin use in america and gaps in patient education (USAGE): An internet-based survey of 10,138 current and former statin users. J Clinical Lipidol. 2012;6(3):208-215.
- Howard JP, Wood FA, Finegold JA, et al. Side effect patterns in a crossover trial of statin, placebo, and no treatment. JACC. 2021;78(12):1210-1222.
- Herrett E, Williamson E, Brack K, et al. The effect of statins on muscle symptoms in primary care: the StatinWISE series of 200 N-of-1 RCTs. Health Technol Assess. 2021;25(16):1-62.
- Cheeley MK, Saseen JJ, Agarwala A, et al. NLA scientific statement on statin intolerance: a new definition and key considerations for ASCVD risk reduction in the statin intolerant patient. J Clin Lipidol. 2022;16(4):361-375.
- Sjölander M, Carlberg B, Norberg M, et al. Prescription of lipid-lowering and antihypertensive drugs following pictorial information about subclinical atherosclerosis: A secondary outcome of a randomized clinical trial. JAMA Netw Open. 2021;4:e2121683.
- Sandhu AT, Rodriguez F, Ngo S, et al. Incidental Coronary Artery Calcium: Opportunistic Screening of Previous Nongated Chest Computed Tomography Scans to Improve Statin Rates (NOTIFY-1 Project). Circulation. 2023;147:703-714.
- Olson KL, Rasmussen J, Sandhoff BG, Merenich JA. Lipid management in patients with coronary artery disease by a clinical pharmacy service in a group model health maintenance organization. Arch Intern Med. 2005;165:49-54.
- Sandhoff BG, Kuca S, Rasmussen J, Merenich JA. Collaborative cardiac care service: a multidisciplinary approach to caring for patients with coronary artery disease. Perm J. 2008;12(3):4-11.
- Blood A.J., Cannon CP, Gordon WJ, et al. Results of a remotely delivered hypertension and lipid program in more than 10 000 patients across a diverse health care network. JAMA Cardiol. 2023;8:12-21.
- Virani SS, Aspry K, Dixon DL, et al. The importance of low-density lipoprotein cholesterol measurement and control as performance measures: A joint clinical perspective from the National Lipid Association and the American Society for Preventive Cardiology. Am J Prev Cardiol.2023;13:100472.. doi:10.1016/j.ajpc.2023.100472
Clinical Topics: Dyslipidemia, Lipid Metabolism
Keywords: Cardiology Magazine, ACC Publications, CM-Sep-2026, Lipids, Dyslipidemia, Guidelines as Topic, Practice Guidelines as Topic, Risk Factors
